During an outbreak, the gap between a vaccine that exists and a vaccine that reaches people is measured in weeks and lives. On 2 September, UNICEF and partner organisations announced a stockpile mechanism intended to help countries access mpox vaccines during outbreaks, presented as a preparedness measure intended to reduce delays and inequity. The design is worth examining, because stockpiles have a mixed record.
What a stockpile mechanism is
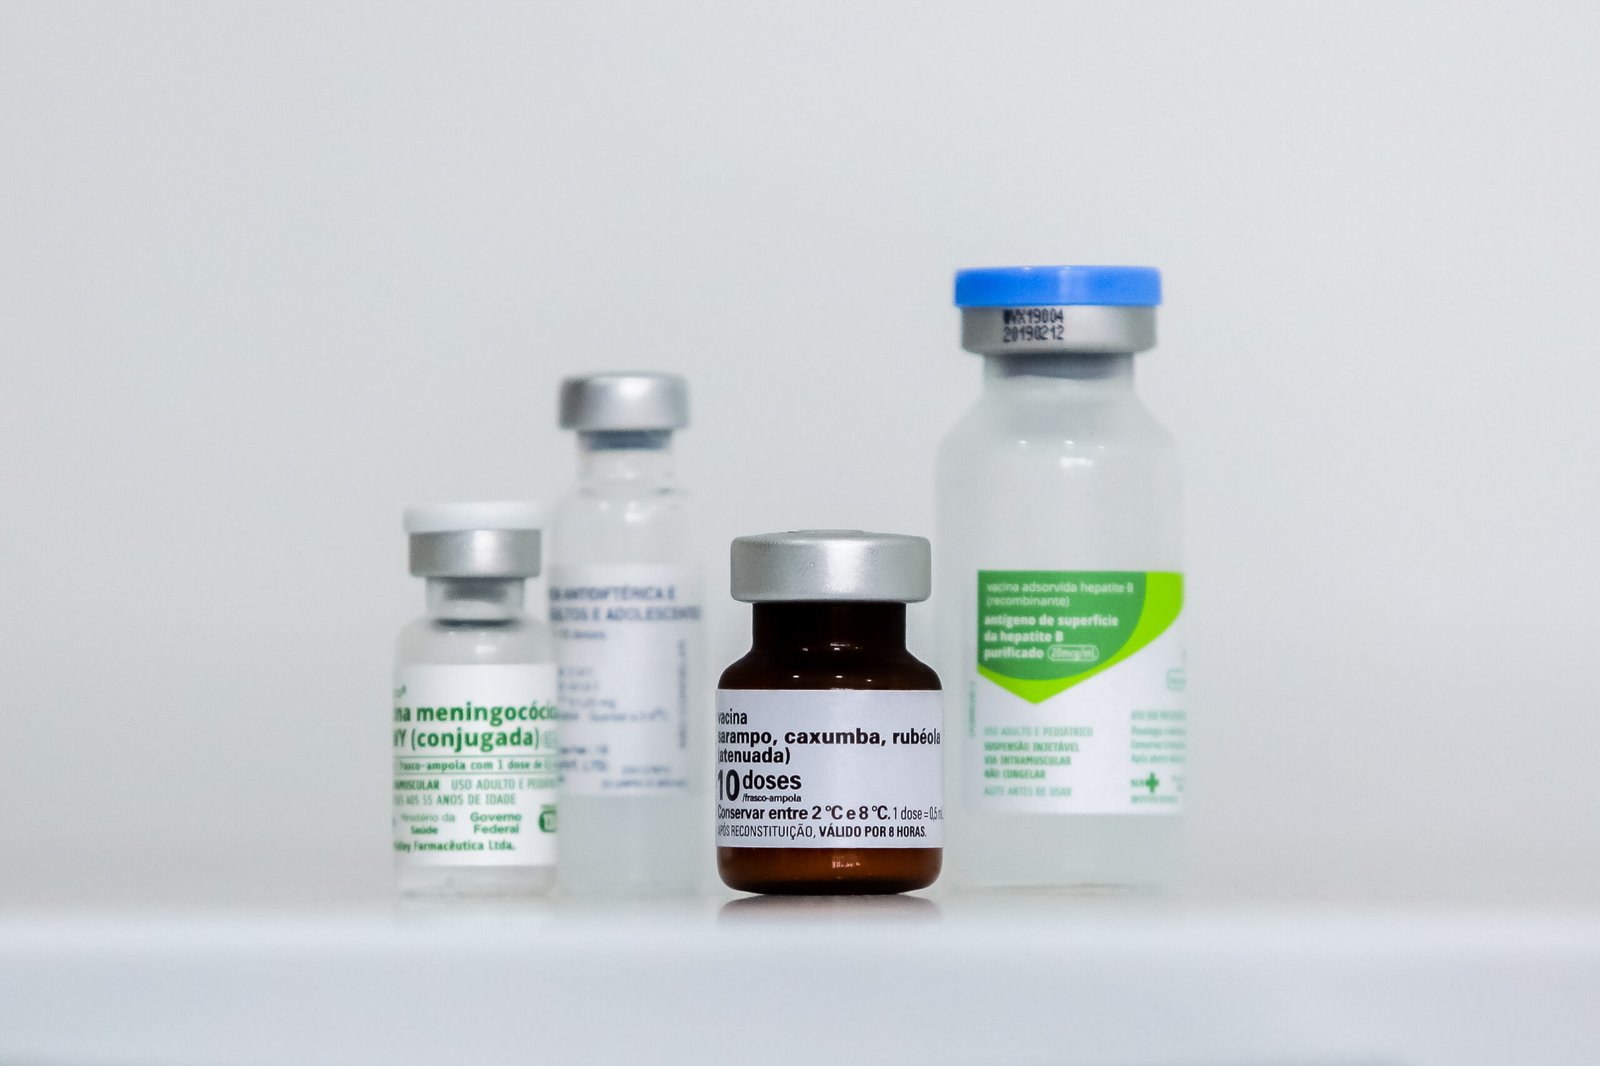
A stockpile holds doses that can be released quickly when an outbreak is declared, rather than requiring each country to procure vaccines in a crisis. The advantage is speed and the ability to direct supplies where they are needed. The disadvantage is cost, because holding doses requires financing, storage and management, and vaccines can expire or become less relevant as the pathogen evolves.
Why mpox is the focus
Mpox outbreaks have occurred in several regions, and access to vaccines has been uneven, with affected countries sometimes waiting while wealthier ones secured supplies. That pattern, familiar from other outbreaks, is what the mechanism aims to address. Equity of access is presented as a central objective, which distinguishes it from a purely commercial arrangement.
What stockpiles can and cannot do
A stockpile can shorten the time between a decision to respond and the arrival of doses. It cannot ensure that doses are administered, because that depends on cold chains, health workers, public information and trust. A vaccine delivered to a capital city does not protect people in a remote district unless the delivery system works. Stockpiles address one part of a longer chain.

The allocation question
When demand exceeds supply, someone must decide who receives doses first. Allocation criteria typically consider epidemiological need, vulnerability and the capacity to administer. These decisions are technically difficult and politically sensitive, and they determine whether the mechanism delivers on its equity objective. The published guidance will reveal the approach.
What the report leaves open
The announcement does not show how many doses will reach each setting or predict future outbreaks. It describes a mechanism. Operational guidance and public-health updates will be the relevant sources for evaluation, and they will show whether the mechanism functions as intended.
The broader preparedness picture
Stockpiles are one element of outbreak preparedness, alongside surveillance, laboratory capacity, clinical care and community engagement. A mechanism that focuses only on vaccines will be less effective than one embedded in a wider system. The initiative’s value depends on how it connects to those other elements.
The next milestones
Operational guidance and public-health updates will be the relevant sources for evaluation. The questions worth following are whether doses are released quickly, whether they reach affected communities and whether allocation follows the stated principles. Those are the measures of whether the mechanism changes outcomes.
The vaccine supply question
Mpox vaccine supply is limited globally, and production capacity cannot be expanded quickly. That constraint is why allocation decisions matter so much and why a stockpile alone does not solve the problem. Increasing supply involves licensing, manufacturing and technology transfer, which take years. In the meantime, the mechanism’s value depends on how efficiently the available doses are used.
How outbreaks are declared
An outbreak declaration is made by national authorities, sometimes with international consultation. The declaration triggers responses and can unlock resources, and it also carries political weight. Delays in declaring can delay the release of stockpiled supplies, which is one reason preparedness mechanisms try to pre-agree the conditions for release rather than negotiating them in a crisis.
The role of regional bodies
Regional health organisations, such as those in Africa, have become more active in outbreak response, coordinating surveillance, laboratory networks and procurement. Their involvement changes the dynamics of access, giving affected regions a stronger voice in decisions that were once dominated by wealthier countries. The stockpile mechanism will operate alongside these bodies, and the relationship will shape how quickly doses move.
The logistics of delivery
Vaccines require cold chains, trained staff and functioning health facilities, and in outbreak settings these are often strained. A stockpile that releases doses quickly still depends on the system that administers them. Investment in delivery capacity, including cold storage and community health workers, is what turns a dose into protection. Mechanisms that focus only on procurement risk leaving the last mile unfunded.
Community engagement
Vaccination depends on trust, and trust is built through community engagement before an outbreak. Where communities have experience of responsive health services, uptake is higher; where they have been neglected or misled, hesitancy is greater. Preparedness therefore includes communication and relationship-building, which are difficult to stockpile and essential in practice.
The mechanism’s long-term value will depend on whether it becomes a routine part of outbreak response or a one-off initiative. Preparedness measures are easy to announce and hard to sustain, because their benefits appear only when they prevent something. Tracking whether the stockpile is replenished, exercised and actually used will show whether the commitment outlasts the announcement.
This report draws on UNICEF.
Image: James Gillray · Public domain · via Wikimedia Commons.